
- Reference Number: HEY1160/2026
- Departments: Neonates, Ophthalmology Department, Orthoptic
- Last Updated: 30 September 2026
Introduction
This leaflet has been produced to give you general information. Most of your questions should be answered by this leaflet. It is not intended to replace the discussion between you and the healthcare team but may act as a starting point for discussion. If after reading it you have any concerns or require further explanation, please discuss this with a member of the healthcare team.
What is Ptosis?
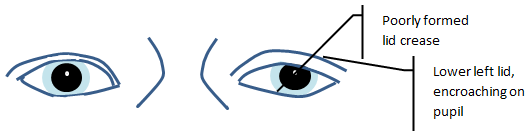
Ptosis is the medical term for drooping of the upper eyelid. It can affect one or both eyes. Ptosis may be congenital (present at birth) or acquired (developing later). The amount of drooping can vary from mild to severe and, depending on the position of the eyelid, may affect vision.
Congenital
Congenital ptosis is most commonly due to the levator muscle, which raises the upper eyelid, not developing normally. It is usually noticed at birth or in early childhood as a droopy or heavy upper eyelid and can vary in appearance. It may be more noticeable when a child is tired or unwell. If one or both upper eyelids are low, a child may raise their eyebrows or lift their chin to see more clearly. This posture can sometimes cause forehead, head or neck discomfort. One type of congenital ptosis is Marcus Gunn ‘jaw-winking’ syndrome, where the eyelid moves when the jaw moves.
Acquired
- Acquired ptosis can occur for a number of reasons, including:
- A problem with the tendon that connects the levator muscle to the eyelid, for example following injury or previous eye surgery. Age-related changes are a common cause in adults.
- Weakness of the eyelid muscles, which can occur in some rare muscle conditions.
- A problem with the nerve that controls the eyelid muscle.
- A mechanical cause that increases the weight of the eyelid, such as a cyst or swelling.
- Trauma or injury.
Can this impact vision and why do I need to attend appointments?
In many children, ptosis does not significantly affect visual development. However, children are not born with fully developed vision, and their visual system continues to develop during childhood. If a drooping eyelid blocks the pupil or interferes with normal visual development, this can lead to amblyopia (reduced vision, sometimes called ‘lazy eye’). Children with ptosis can also have other eye problems, including a squint (strabismus) or a need for glasses (refractive error), which may also affect visual development.
It is important to attend Orthoptic appointments so that the Orthoptist can monitor how vision is developing in both eyes. The assessment may include checking your child’s vision, eye position and whether glasses or treatment for amblyopia are required. The position and movement of the eyelid will also be monitored by the eye care team. Please contact the department for advice if you notice a significant or sudden change in the eyelid position or your child’s vision.
What is the treatment?
Many children with ptosis do not require treatment and can be monitored, particularly when the eyelid is not affecting vision. If visual development is affected and vision is reduced in one eye, your child may require amblyopia treatment to encourage visual development in the weaker eye. This may include glasses and/or patching or other treatment, depending on your child’s individual needs. The Orthoptic team will discuss this with you at your appointment.
Surgery to raise the eyelid may be considered if the ptosis is interfering with vision, if your child is adopting a significant chin-up head position, or because of the appearance of the eyelid. If the eyelid is obstructing the pupil and putting visual development at risk, surgery may be recommended at an earlier age. If vision is developing normally, surgery can often be delayed and the timing discussed with you and your child. Children usually have ptosis surgery under a general anaesthetic. The type of operation depends on the severity of the ptosis and how well the eyelid muscle works, and the ophthalmologist will discuss the most appropriate option with you.
Are there any complications or risks?
Ptosis surgery is complex and it is not possible to guarantee a perfectly symmetrical eyelid position or appearance. Most children have a satisfactory improvement, but further surgery may sometimes be required.
Possible complications include the eyelid being too high (overcorrection) or remaining too low (undercorrection), asymmetry between the eyelids, or an irregular eyelid contour. The eyelid may not move normally when looking down (lid lag) and, particularly after surgery, it may not close completely. This can cause the surface of the eye to become dry or irritated and may require treatment. Other possible surgical complications include bleeding, infection and scarring. The ptosis can recur in the future and further surgery may be needed. Your ophthalmologist will discuss the benefits, risks and alternatives in more detail if surgery is being considered.
Should you require further advice on the issues contained in this leaflet, please do not hesitate to contact the Orthoptic Department on Tel: 01482 816605.
General Advice and Consent
Most of your questions should have been answered by this leaflet, but remember that this is only a starting point for discussion with the healthcare team.
Consent to treatment
Before any doctor, nurse or therapist examines or treats your child, they must seek your consent or permission. In order to make a decision, you need to have information from health professionals about the treatment or investigation which is being offered to your child. You should always ask them more questions if you do not understand or if you want more information.
The information you receive should be about your child’s condition, the alternatives available for your child, and whether it carries risks as well as the benefits. What is important is that your consent is genuine or valid. That means:
- you must be able to give your consent
- you must be given enough information to enable you to make a decision
- you must be acting under your own free will and not under the strong influence of another person
Information about your child
We collect and use your child’s information to provide your child with care and treatment. As part of your child’s care, information about your child will be shared between members of a healthcare team, some of whom you may not meet. Your child’s information may also be used to help train staff, to check the quality of our care, to manage and plan the health service, and to help with research. Wherever possible we use anonymous data.
We may pass on relevant information to other health organisations that provide your child with care. All information is treated as strictly confidential and is not given to anyone who does not need it. If you have any concerns please ask your child’s doctor, or the person caring for your child.
Under the General Data Protection Regulation and the Data Protection Act 2018 we are responsible for maintaining the confidentiality of any information we hold about your child. For further information visit the following page: Confidential Information about You.
If you need information about your child’s (or a child you care for) health and wellbeing and their care and treatment in a different format, such as large print, braille or audio, due to disability, impairment or sensory loss, please advise a member of staff and this can be arranged.
